From Shin Splints to Marathon in 30 Days

From Shin Splints to Marathon in 30 Days
Ouch. I had never actually considered how painful shin splints or medial tibial stress syndrome (mtss) is!
Really painful by the way.
Firstly, thank you to Tom Goom, for his help when I was in a pure running patient denial, and secondly for allowing me to write up this case study, for his awesome resource of a website.
So yes, the physio training for the marathon got mtss. He should have known better. And maybe I should have, I was trying to run Brighton marathon in a decent time, whilst also competing in the basketball season, two very high load activities and if you read here the two most likely for stress fracture in the lower extremity.
Thankfully I didn’t have a stress fracture though, and that is where the story begins.
Day 0, 16 weeks into a 20 week marathon training programme of four runs a week, and three quarters of the way through the basketball season.
It was Cheltenham Race Festival Gold Cup Day, out for a few waters and a flutter for my 30th Birthday, smartly dressed, peaky blinders cap on and a pair of Chelsea boots, which I had worn a lot but felt a little bit uncomfortable to put on. By the end of the day I was hobbling home.
Day 1, a 20 minute run to loosen the legs before a half marathon tomorrow, hobbled the whole way but completed. Only to despair on the way back that I might not be able to do the half marathon, but why…why have I got shin splints I said to myself.
And this is a key question, because even knowing what I know I could not initially work it out. My running plan was on point, and I was 16 weeks into running alongside basketball. I can understand how hard it is for our patients when they tell you that nothing has changed and they have not done anything different.
So I told myself it will be gone soon, and of course posted about it on social media. Which Tom kindly picked up, and persuaded me to stop thinking like a patient and start thinking like a physio again.
My pain was anterior tibia, I was hobbling badly, hardly getting around, and pain was prominent at rest and keeping me up at night. Objectively, I had pain on impact, unable to single leg hop and pain on palpation. If a patient came to me with those symptoms I would have them in a boot and off for some further investigations. And that is what I did, boot went on, on day 3, thanks to Tom for pointing that out.
I am fortunate I work in private practice, and with the help of my practice manager had the MRI on day 6. Wright et al (2016) have a very good algorithm to help decision making in clinical practice, and if you are suspecting a stress fracture in a high risk area then an MRI is the desired investigation. For more on high and low risk areas read here. Amazingly, 85% of stress fractures go undetected on the initial radiograph and 50% go undetected on follow-up radiographs (Moran et al, 2008), suggesting a high number of false negatives.
The results arrived on day 7:
“There is evidence of medial tibial stress syndrome seen bilaterally significantly worse on the left side. There is also a sprain seen in the tibialis anterior muscle on the left side”
Mtss confirmed. Great! Boot came off that day, only to go back on that night…mtss is painful!!
And I still kept asking myself why. 60-70% of running injuries are down to training error, “but my programming was on point I thought”, but changes in load can affect you for up to 4 weeks, so I took a look at that. And there it was, some interesting changes in my load which I completely failed to see, and brings me back to our expectation of patients and it being a big ask when we are asking them to consider or recognise changes in load.
My time on court had increased over the last 2 weeks. Normally it is either a game or training, not often both, and recently we had had a lot of games which means between 25-35 minutes of on court time. However the last two weeks leading up to the pain was two training sessions (within 8 days each other). Training means 2 hours of non stop time on the court, which also happened to coincide on the weeks of my longest runs. How did I miss that!
As a side note, I find getting patients or athletes to do something like this and go over their last four weeks can be a really helpful tool both for your understanding as a physio treating them but also for their understanding.
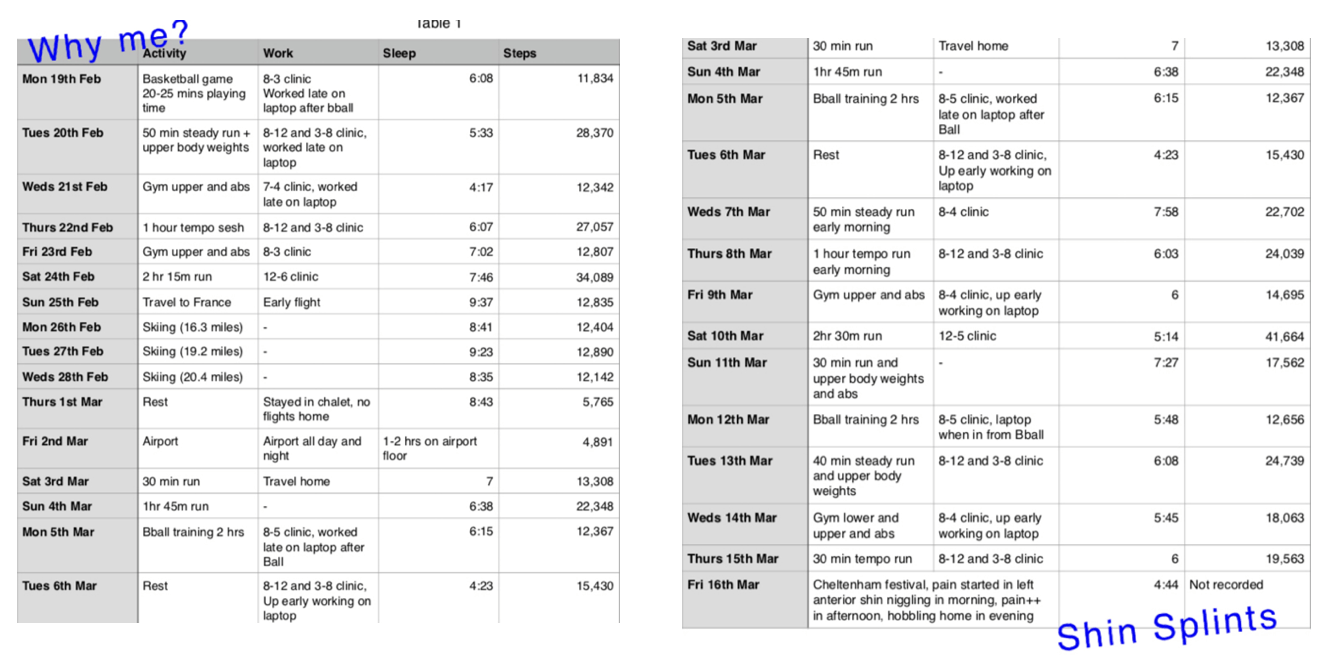
The other point to consider is my recovery. I had also been working a lot, both time in clinic and away from it. This led me to working late and getting up early to either work or squeeze in a run. As you can see this shows some rather erratic sleep patterns, and certainly not enough for recovery. Tom wrote a great piece here on sleep not so long ago. The key take away for me at this time was the military study which suggested sleep may be important for bone health, and sleep deprivation possibly being a factor in the development of bone stress injuries. The other key point was from research from Bonnar et al (2018) is that adults need 7 to 9 hours of sleep but athletes 9-10 hours….I’m not an athlete but the question is am I reaching the activity levels to be considered to be training at an athletic volume?
With this in mind, as part of my rehab and now my life I have changed my sleeping habits. I can’t get up any later but I can make sure I am in bed an hour earlier, even if not sleeping what I have found is it means I drop off earlier and my trusty smart watch tells me I am almost achieving a extra hour of sleep a night now.
So what about the rest of the rehab. It was tricky. Mtss is irritable. We had lots of conversation on twitter about how the best way to rehab was and the consensus was a gradual increase in load with the inclusion of some multidirectional loading. But how far can we poke the bear. Well I found in the early stages not far. If I pushed past a 1-2/10 I really suffered and continued to hobble around. Whereas if I felt it at a 1-2/10 and stopped then I would be ok. This was most felt with me in a step and land exercise which took me 3 days to achieve because pain limited.
Once I then got to the later stages of hopping, multi-directional hopping and change of direction I actually found I could push it to a 3-4/10 and be ok after. Now I can’t find a great deal of evidence on this, so this is very much my anecdote of me as a case study!
Here are some examples of routines I went through:
Day 9: https://instagram.com/p/BgveTU6B40s/
Day 11: https://instagram.com/p/Bg0X0CBBeNl/
Day 12: https://instagram.com/p/Bg38wnYBpcp/
Day 14: https://instagram.com/p/Bg9N_kBhlu_/
And then it was back to running! Now everything in me as a physio tells me to build up slowly. My normal planning for patients is three minute progressions, every other day, working on a pain continuum of 0-10 with 0-3/4 being our safe zone. Any more we reduce back, do a couple of runs at that level and then try to progress again. Perfect right?
However, the runner in me had other ideas. And I had two weeks to Brighton Marathon, it was boom or bust. So I started tentatively, Day 15 I did 9 minutes. I was aiming for 10 minutes but thought I could feel it. Rumination: the fear is definitely real.
And then the accelerated programme kicked in. Day 16: 30 minutes, day 18: 45 minutes, day 20: 60 minutes, day 22: 90 minutes. And then I was into my taper for the marathon week.
When I look back at that, it scares me, crazy quick progression that I would never do with a patient, but it worked….and I guess my learning from that is, sometimes the body can adapt much quicker than we maybe give it credit for.
Day 30, Brighton Marathon rolled around and was relatively successful. My adjusted injury time goal was achieved and I went round in 3:35, fatiguing in the last 10km having missed my two long runs, but most importantly a successful rehab phase, lots of learning and we survived to run another day.